Pain sits at the facility of nursing method more often than many people understand. On a medical ward after 7 p.m., a child with a forearm fracture will certainly not consider the IV pump or the actors, they will certainly see your face for cues that points are going to be fine. In an aged care center, the local that quit strolling last month might have improperly acknowledged neuropathic pain. In an active emergency situation department, a paramedic handover for a crush injury rests on just how quickly and securely you can titrate analgesia. The skill set that underpins those moments is learnable, improvable, and certifiable, and nurses that buy organized pain monitoring training typically really feel the difference by the next shift.
This post unloads what high‑quality pain education appears like for registered nurses, exactly how certification programs establish capability, and where a short program can genuinely shift method. It likewise explains just how device codes like PUAEme008 associate with emergency situation discomfort competencies, and exactly how the appropriate pain monitoring qualification course advantages not only nurses however physiotherapists, paramedics, and interprofessional teams.
What competence suffering management truly means
Competence is not a solitary skill, it is a mix of expertise, judgment, and implementation under stress. When I mentor early‑career registered nurses, I search for five capacities that signify real discomfort monitoring competence.
First, precise analysis. This exceeds asking "what is your pain from absolutely no to ten." It suggests choosing the best device for the scenario, such as a Numeric Rating Range for a lucid adult, the Wong‑Baker deals with scale for a kid, or the Abbey Discomfort Scale for an individual with innovative mental deterioration. It implies identifying the limits of essential signs as discomfort proxies and correlating the story with the examination.
Second, pharmacologic fluency. Safe, efficient titration of opioids requires greater than "start low, go slow." It calls for understanding equianalgesic dosing, the difference in between hydrophilic and lipophilic opioids, ceiling impacts for tramadol or tapentadol, and how renal or hepatic impairment modifications your alternatives. It additionally means being comfortable with complements like ketamine for opioid‑tolerant people, or clonidine as part of a multimodal plan, while expecting hypotension or bradycardia.
Third, non‑pharmacologic technique and timing. Nurses control the environment and the procedure around pain. The peaceful area, the warm covering, the splint placed before the transfer, the ice prior to the swelling tops, the cognitive reframing during dressing adjustments-- these are not niceties; they are evidence‑based analgesic interventions.
Fourth, threat acknowledgment. High‑risk situations have patterns: the hypoxic COPD patient with IV morphine; the sickly person with a femoral fracture and borderline blood pressure; the person on high‑dose methadone for opioid use disorder offering with acute abdominal pain. Competence implies anticipating breathing clinical depression, delirium, or withdrawal, aligning tracking and rescue meds, and understanding when to escalate.
Fifth, communication and documents. Clear pain strategies transform results. When the analgesic ladder is set out in the notes with targets, periods, and rescue limits, handovers are more secure and patients report far better complete satisfaction and function. Discomfort is a signs and symptom, but it is also a data stream. Proficiency means reading it and creating it down in a manner coworkers can act on.
Formal discomfort administration training courses that cause a discomfort monitoring certificate should purposefully construct these 5 pillars, not simply talk on the that ladder.
Where certificate courses fit and why they help
On the‑job learning issues, but it leaves spaces. A certification program suffering management, especially one developed for registered nurses, puts framework around the art and offers shared language throughout a team. The most effective pain administration training programs combine pre‑reading, case‑based workshops, simulation with comments, and assessment tied to expertise frameworks.
The return on investment shows up quickly. Medication mistakes drop. Patient‑controlled analgesia comes to be less scary for team and much safer for clients. Nurses feel more positive setup expectations with households, like clarifying that the objective is enhanced function and remainder, not overall removal of pain, and that non‑drug procedures are not optional add‑ons. For supervisors, a discomfort management certificate course offers evidence for credentialing and meets continuing specialist development needs in a manner that touches everyday care.
Programs vary in size. Short programs hurting administration may run four to 8 hours and concentrate on assessment tools, multimodal essentials, and typical risks. Longer pain administration accreditation training courses extend over numerous weeks with self‑paced components on pathophysiology, opioid stewardship, online pain management training neuropathic pain, and complicated scenarios like burns or sickle cell situation. Both belong. Brief focused training matches a ward rollout or refresher course. An extensive certificate fits a registered nurse taking on a pain resource function, an educator, or a person working in high‑acuity or specialty settings.
The emergency situation context and PUAEme008
Emergency pain management is a self-control of its very own, with speed, unpredictability, and crowded areas. Prehospital and ED teams require durable training that blends fast analysis, protocol‑driven pharmacology, and guidebook methods that get time prior to pain management certification training programs definitive treatment. In several educational programs, you will certainly see system codes like PUAEme008 connected with emergency expertises. In some territories, PUAEme008 Give Discomfort Administration explains the skills and expertise called for to analyze pain, select suitable non‑pharmacological and medicinal strategies, provide or aid with analgesics under clinical administration, keep an eye on the person, and hand over treatment effectively.

If your company references PUAEme008 offer pain administration, confirm the present version and local range, as system codes and proof demands can change with training plan updates. In method, a PUAEme008 give discomfort management course need to cover:
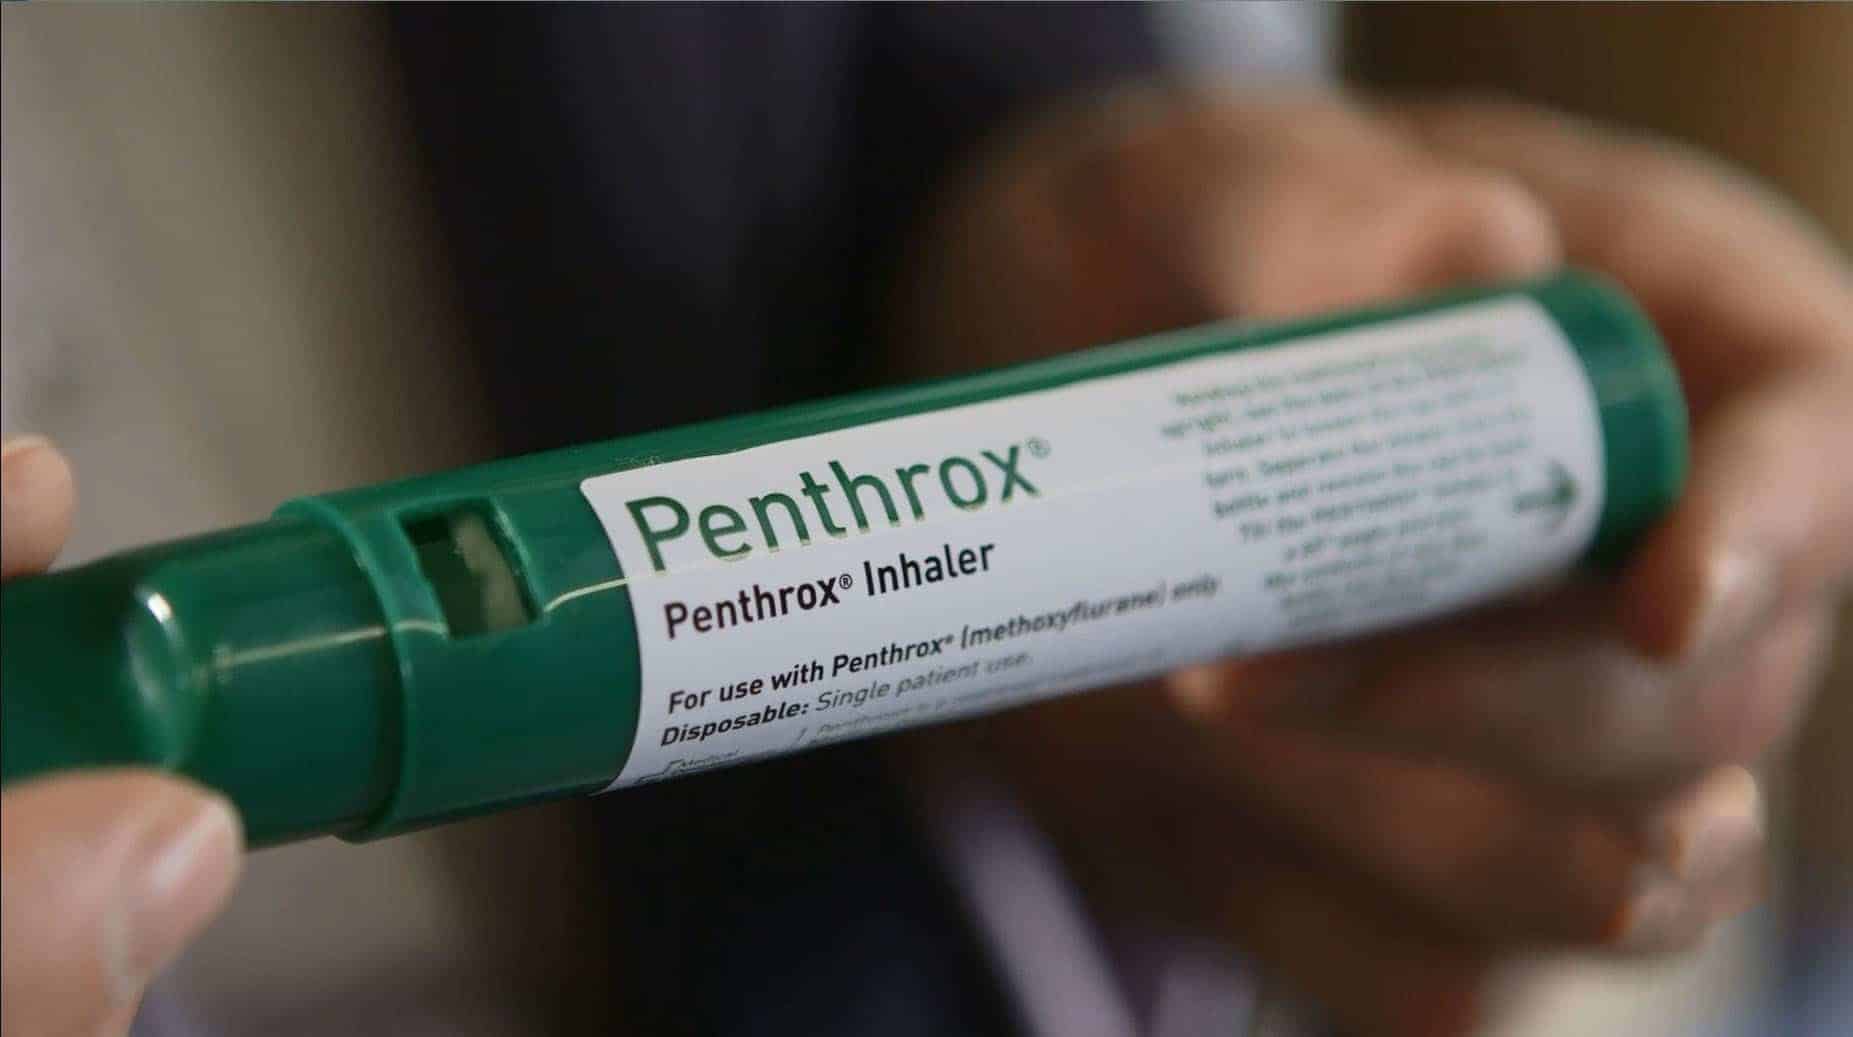
- Rapid discomfort assessment in loud, time‑limited environments, with alternatives for non‑verbal patients. Indications, doses, contraindications, and checking for typically utilized agents in the field or ED triage, such as methoxyflurane, intranasal fentanyl, nitrous oxide, and oral analgesics. Splinting, placing, and cooling or warming up methods that materially minimize pain before analgesia. Safety methods, consisting of oxygen use with inhaled agents, ecstasy danger in older grownups, and paperwork that sets the obtaining team up for smooth continuation of care.
When straightened well, a PUAEme008‑based brief training course incorporates efficiently right into ED induction and paramedic upskilling and offers a defensible standard for proficiency sign‑off.
Building blocks of effective registered nurse pain education
The ideal discomfort management courses for nurses share common features also when supplied in various styles. First, they adapt web content to the medical atmosphere. A medical ward does not need the exact same circumstances as a pediatric oncology device, and a country ED with minimal imaging and delayed transfers has various threat points than a city injury center.
Second, they utilize situations, not just slides. I bear in mind a situation made use of in our training that followed an opioid‑naïve postpartum woman who created respiratory system anxiety after repeat IV morphine boluses for laceration pain. The group needed to map a much safer plan that made use of arranged nonsteroidals, regional block appointment, and nurse‑activated naloxone parameters. That solitary situation changed how numerous people created post‑cesarean orders for years.
Third, they determine capability with useful jobs. Can you set up PCA with the appropriate lockout and paper sedation scores effectively? Can you chat a person with using a FACES range when English is not their mother tongue? Can you identify neuropathic features in a patient with diabetic issues and adjust the strategy as necessary? Observation lists defeat multiple‑choice alone.
Fourth, they acknowledge prejudice. Studies reveal that client demographics influence discomfort scores and treatment choices in means we would rather not confess. Great courses require reflection and give manuscripts that standardize care, which minimizes disparities.
Fifth, they map to credentialing. A discomfort management qualification that mentions which proficiencies were examined, and at what standard, is more useful than a certification of attendance. Registered nurses are worthy of recognition that equates to functions and pay, not simply a line in a portfolio.
Pharmacology that registered nurses really use
Every registered nurse who finishes a pain administration certification training course ought to come away with a functional, nuanced understanding of analgesics in actual setups. That consists of understanding when to pick oral over IV, how to pre‑empt pain with normal dosing, and how to pivot when the very first attempt fails.
Nonsteroidal anti‑inflammatory medicines lower prostaglandin manufacturing and are especially helpful after orthopedic and oral procedures. The trade‑off is kidney perfusion and blood loss danger, specifically in older grownups and those on anticoagulants. Acetaminophen is a foundation medicine, yet its ceiling dose matters, and we routinely find duplicate therapy when a client gets a mix opioid tablet plus routine paracetamol.
Opioids remain needed in moderate to serious acute pain. Qualified titration is not a guessing video game. For IV morphine, initial boluses of 2 to 2.5 mg with reassessment every 5 to 10 mins offer fine control. If the individual is opioid forgiving, the increments and ceiling shift, but the principle holds. For intranasal fentanyl, typical ED dosages are 1.5 micrograms per kg as much as institutional optimums, with repeat application based upon impact. A pain management program ought to infuse regard for opioid kinetics, cross‑tolerance, and the functional use sedation scales like Pasero or RASS as guardrails.
Adjuvants change lives in neuropathic pain. Gabapentinoids, tricyclics, SNRIs, and topical representatives like lidocaine patches can be definitive, however they carry adverse effects that nurses have to keep track of and explain. Topical NSAIDs aid in localized musculoskeletal pain without system‑wide exposure. For complex acute pain, low‑dose ketamine infusions under method, or alpha‑2 agonists, can minimize opioid dose. Nurses are the ones that observe the early tremors of ecstasy or the creeping blood pressure decline and act before it ends up being a crash call.
Regional anesthesia is its own cosmos, but every nurse should recognize with common blocks in their unit, from adductor canal blocks in knee surgical treatment to fascia iliaca blocks in hip fractures. Recognition of anesthetic systemic toxicity belongs to safety and security training, as is access to intralipid protocols.
Non medicine methods that in fact make a dent
Skeptics occasionally disregard non‑pharmacologic interventions as soft medicine, but they work when supplied with intent. Proper arm or leg elevation and compression reduce edema and nociceptor activation. Splinting a broken rib with a cushion throughout coughing, and mentor paced breathing, can alter a patient's day. Warm decreases muscle mass spasm; cool decreases swelling; both require timing and skin checks.
Cognitive treatments are not the sole province of psychologists. Grounding techniques during clothing changes, straightforward led imagery, and coaching that reframes discomfort as a manageable signal, not a tidal bore, boost analgesic feedback. For pediatric patients, play treatment and diversion exceed another IV bolus in certain treatments. Rest is analgesic, noise is the opponent, and nurses are the designers of both.
Physiotherapists are important companions. Pain monitoring training courses for physio therapists typically highlight rated exposure, pacing, and functional goals. When registered nurses and physio therapists align language and timing, people set in motion faster with much less distress. Interprofessional brief programs in pain administration build this common strategy and minimize combined messages.
Recognizing and managing special populations
Older adults metabolize medications in a different way, and their minds are prone to ecstasy. A secure plan typically starts with arranged acetaminophen, careful NSAID use if kidney function permits, low beginning dosages of opioids with tight review, and aggressive non‑drug steps. I have seen older people with hip cracks turn around simply from a fascia iliaca block plus cozy coverings, gentle positioning, and regular mentoring to take a breath and move.
People with opioid use disorder offer a familiar challenge. Under‑treating their acute pain due to preconception or concern causes acceleration habits, bad outcomes, and conflict. The far better course is sychronisation with dependency services, extension of methadone or buprenorphine when possible, enhancement of greater opioid dosages to get rid of resistance in the short term, and clear plans for taper. Training courses that include these scenarios boost staff comfort and person trust.
In pediatric settings, dose arrays are weight‑based and courses issue. Intranasal analgesia radiates here. Teaching moms and dads how to use FACES or FLACC scores and what to expect from multimodal analgesia brings them into the group. A pain management training program that consists of pediatric modules pays for itself the following school holiday when broken arms fill the waiting room.
For patients with interaction barriers or cognitive problems, confirmed empirical devices like PAINAD or Abbey are vital. Staff require to recognize the mistakes, like misinterpreting uneasyness from urinary system retention as discomfort, or missing out on discomfort that offers as withdrawal or reduced activity.
Assessment and documents that people can use
Documentation is not a bureaucratic workout. Great notes develop continuity. The most effective pain plans have clear targets, such as "Goal: discomfort ≤ 4 at remainder, ≤ 6 on activity; client able to sit out of bed for meals." They specify time‑bound actions: "If discomfort remains ≥ 7 thirty minutes after 2 mg IV morphine, administer extra 1 mg every 5 to 10 mins to an optimum of 6 mg, reflecting on sedation with Pasero scale." They advise the following nurse of dangers: "Display for breathing price << 10 per min; if happens, stop opioid and call medical officer; consider naloxone 40 micrograms IV increments." They note non‑drug procedures already tried and the patient's feedback, so associates do not repeat failures.</p>
Pain review timing varies by course and agent. After dental analgesia, reassess in 45 to 60 mins. After IV bolus, reassess in 5 to 10 mins. After regional anesthetic, reassess feeling and electric motor function per protocol. Several wards fall short at the review action. A pain monitoring certificate program that drills the timing and the why will avoid the persistent cycle of "gave something, moved on, forgot to examine."
Course option: what to look for
There is no scarcity of programs marketed as pain management programs for nurses. Quality differs. A detailed evaluation saves time and prevents stress. Try to find external alignment with identified structures, such as nationwide discomfort societies or expertise requirements utilized in your country. Examine the deepness of material beyond the fundamentals. Does the program get involved in opioid conversion, ecstasy avoidance, and regional anesthesia safety and security, or does it stop at acetaminophen plus morphine?
Ask regarding analysis. A discomfort management accreditation that requires an instance write‑up, a simulated scenario, and a racked up observation of method lugs more weight than one that uses just on-line quizzes. Inspect the professors. Programs taught by a mix of nurses, anesthetists, pain doctors, and physiotherapists bring more comprehensive point of views and more realistic cases.
Flexibility matters in nursing timetables. The very best pain monitoring training for nurses supplies modular online concept with brief in‑person abilities sessions and local mentors for expertise sign‑off. If your company needs an emergency situation emphasis, focus on carriers that can deliver an emergency pain monitoring component or a PUAEme008 offer pain management program pathway.
Costs range commonly. A half‑day brief course could set you back much less than a change of overtime. A full pain management certification training course with evaluation, feedback, and an identified certificate will set you back more and may be qualified for professional development financing. When budgets are tight, train a staff of discomfort champions that can advisor others on the floor.
Implementation lessons from actual wards
I have turned out discomfort education and learning on surgical and clinical devices, and the very same practical lessons turn up each time. Beginning with the information from your own solution. Pull five current charts where pain administration went inadequately and anonymize them for conversation. Team interaction climbs when the instances look acquainted. Mix quick victories with deeper change. Quick wins consist of standardizing discomfort scales by person team, uploading rescue dosing algorithms at medicine stations, and making cold pack and warmth packs easy to find.
Deeper modification entails order sets and methods. Work with prescribers to systematize multimodal pre‑emptive analgesia for typical treatments and to embed reassessment timing motivates in electronic documents. Recognize a couple of registered nurses per change as pain sources that can be asked for recommendations. Monitor for unintended effects, such as a rise in irregular bowel movements from better opioid initiation, and respond with automatic digestive tract routines and client education leaflets.
Measure what matters. Numeric pain ratings are only part of the picture. Track practical results: time to first mobilization, capacity to rest via the evening, participation in physical rehabilitation. Share stories of success and near misses out on in huddles. A discomfort management training program sticks when it becomes part of the device's language.
Interprofessional benefit, not just nursing
Although this post focuses on discomfort management training for registered nurses, the most effective programs explicitly welcome physiotherapists, pharmacologists, and junior medical professionals. Pain management training courses for physio therapists emphasize graded exposure and movement strategies that rely on collaborated analgesia. Pharmacologists include needed rigor to medicine settlement and changes for renal or hepatic impairment. When teams educate with each other, you obtain faster PCA troubleshooting, better pre‑op counseling, and fewer mixed messages to people like "stay in bed" from someone and "activate per hour" from another.
For ED and prehospital solutions, interprofessional training is not optional. A paramedic with a PUAEme008 background and an ED nurse with a strong pain management certification framework will certainly hand over and proceed treatment seamlessly, decreasing duplication and delay.
Certification versus proficiency: making both count
A pain management certification signifies training course completion. Proficiency implies you can do the work to requirement under genuine conditions. The objective is both. Programs must provide the certificate and an expertise checklist tied to visible actions: proper use discomfort scales, suitable medication selection and titration, secure surveillance, effective non‑pharmacologic interventions, and clear documentation.

Managers can utilize these lists for local sign‑off, linked to benefits like hanging ketamine infusions, initiating nurse‑driven analgesia methods, or handling PCAs. Nurses can keep them in their profiles for recredentialing and task applications. With time, refreshers keep the edge. Discomfort method modifications: new guidelines for opioid stewardship, new local blocks, far better delirium prevention. Set a cycle, typically 2 to 3 years, for a discomfort administration accreditation training course update, with shorter refresher courses in between.
Two sensible checklists you can use tomorrow
- Rapid ED discomfort plan at triage: 1) Identify most likely discomfort mechanism and extent, 2) Select a route that works now, 3) Apply a physical treatment immediately, 4) Document reassessment time, 5) Flag risks and monitoring needs. Ward based multimodal package after significant surgical treatment: 1) Arrange non‑opioids around the clock unless contraindicated, 2) Take into consideration regional or neighborhood choices early, 3) Make use of low‑dose opioids for advancement with clear ceilings, 4) Mandate reassessment times and sedation scoring, 5) Pair analgesia with mobilization and digestive tract regimen.
These checklists are beginning points, not alternatives to formal training. They function best when woven right into protocols and reinforced throughout handovers.
Where to go next
If you are a nurse mapping your advancement for the coming year, consider a layered approach. Begin with a short training course suffering administration that fits your existing unit, after that plan for a much more comprehensive pain administration qualification program within 6 to twelve months, ideally one that consists of simulation and assessed expertises. If your duty consists of triage or ambulance user interface, choose an emergency situation discomfort management component or a PUAEme008 give pain monitoring pathway acknowledged in your region.
For teachers and supervisors, build a regional curriculum that blends inner training with outside accreditation. Straighten it to your medicine formulary, your tracking devices, and your client populace. Track results, share victories, and review content annually.
The job is worth it. When an anxious individual unwinds because you clarified the plan and the plan works, when a youngster laughs throughout a procedure since your diversion techniques landed, when an older grown-up avoids ecstasy because your group well balanced analgesia and vigilance, you really feel the difference. Discomfort monitoring training for registered nurses is not just a certificate on a wall surface. It is a set of expertises that alter the day for the person in front of you, and for the registered nurse who wants to go home understanding they did right by them.